On This Page – Quick Medical Summary
Why your doctor may want your TSH lower than normal
A low TSH on your lab report after treatment for differentiated thyroid cancer can be deliberate. This guide explains why, and how targets are set today.
If you just finished surgery or RAI
Start with how suppression works. Then see how your response to treatment shapes your goal.
If you’re years out and still suppressed
Jump to the 2025 guideline changes and the side-effects section. Current ATA guidance holds that most people with thyroid cancer don’t need very strong suppression for life.
Not diagnosed, but worried about a lump? Begin with thyroid cancer symptoms and the tests that find it.
The outlook is usually excellent, because most cases are papillary cancers found while still confined to the thyroid. The American Cancer Society’s thyroid cancer survival statistics break down the figures by stage.
ℹ️ Medical Disclaimer: This article is general education about thyroid cancer follow-up. It does not diagnose any condition, set a TSH target, or recommend a levothyroxine dose, treatment, procedure, or insurance decision. Your TSH goal depends on your pathology, your response to treatment, and your other health conditions, so review any change with a board-certified endocrinologist or your thyroid cancer care team before acting.
Why TSH is suppressed after thyroid cancer
TSH is suppressed after thyroid cancer because this hormone can raise the chance that remaining thyroid cancer grows or recurs, so doctors lower it with thyroid hormone pills.
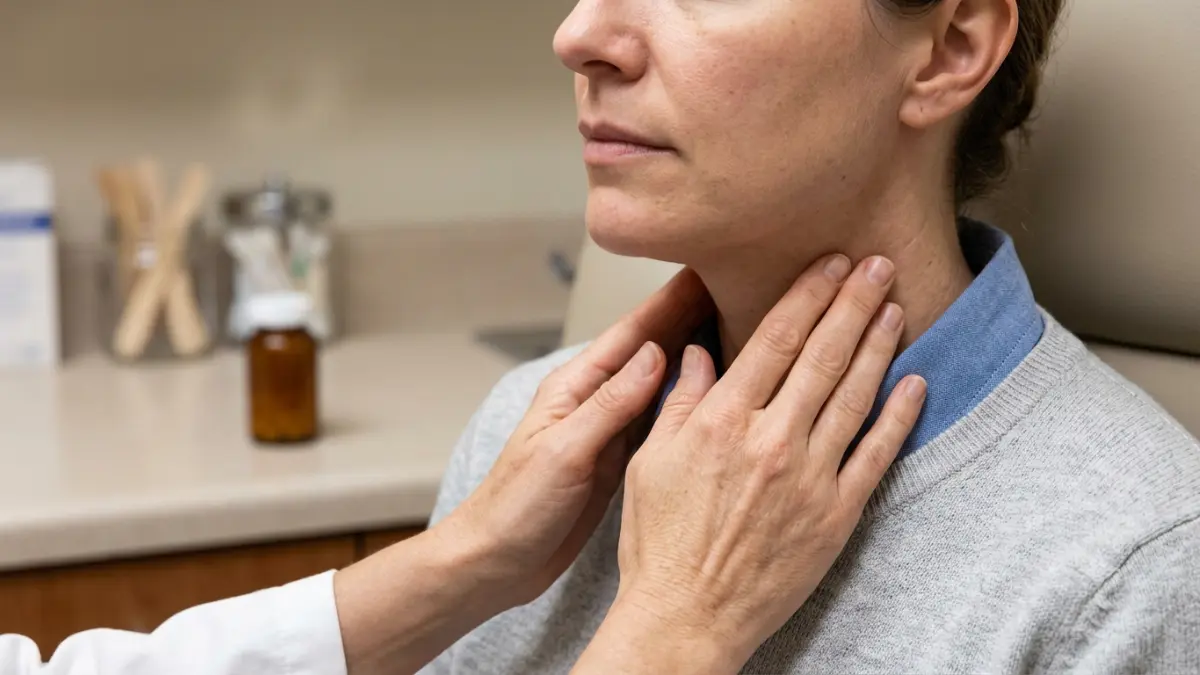
How TSH can affect remaining cancer cells
🔬 How It Works: TSH is the pituitary gland’s signal telling thyroid tissue to work and grow. Differentiated thyroid cancer cells carry TSH receptors and respond to that signal by multiplying. Levothyroxine makes the pituitary sense plenty of hormone, so it sends less TSH.
In most people, a low TSH suggests an overactive thyroid or too high a hormone dose. In cancer follow-up, it can be the planned effect of treatment.
Replacement dose vs suppressive dose
After thyroid surgery, everyone except people who had a lobectomy needs thyroid hormone replacement. A suppressive dose goes further and holds TSH below the normal range. The National Cancer Institute’s thyroid cancer treatment summary describes both roles.
What changed in the 2025 ATA TSH suppression guidelines
The 2025 ATA guidelines replaced most fixed TSH numbers with two goals, within or below the normal reference range, set by your response to treatment.
| Guideline | How the goal is set | Example targets | Key Clinical Detail |
|---|---|---|---|
| 2015 ATA | Initial recurrence risk, adjusted at follow-up | Below 0.1 mU/L for high risk; 0.5–2 mU/L for low/intermediate risk with excellent response | Specific numeric cutoffs |
| 2025 ATA | Ongoing response to therapy | Normal range or below normal range | Undetectable TSH no longer advised |
| 2025 NCCN | Risk and disease status | Below 0.1 mU/L with structural disease; 0.1–0.5 mU/L with biochemical disease only | Keeps numeric cutoffs |
Sources: ATA 2015 recommendations as summarized in Cancer (2017); Ringel et al., Thyroid 2025; NCCN 2025 as summarized in Endocrine Practice (December 2025).

The old approach: targets by initial risk
Previously, the risk assessed right after surgery drove specific numeric goals.
The new approach: normal vs below normal
The expert panel chose broad goals because evidence on exact numbers was inconclusive or conflicting. It also dropped complete suppression to an undetectable TSH. The abstract of the 2025 American Thyroid Association guidelines is available on PubMed.
Where NCCN still differs
NCCN still uses numeric cutoffs, so your team may follow either framework.
How your response to treatment sets your TSH goal
Under the 2025 ATA guidelines, the TSH goal after total thyroidectomy depends on your response to therapy. For an excellent or indeterminate response, the goal is TSH within the normal reference range. For a biochemically or structurally incomplete response, it is below that range.
Excellent or indeterminate response
Broadly, excellent means tests show no sign of remaining cancer, and indeterminate means findings are unclear. For low-risk survivors here, the goal uses the lab’s assay-specific reference range.
Biochemical or structural incomplete response
Biochemical means blood markers suggest disease that imaging can’t see. Structural means disease is visible on scans.
After a lobectomy only
After hemithyroidectomy, only two categories apply: excellent and structurally incomplete.
Is 5 years of suppression still standard?
No. Guidelines no longer explicitly advise up to 5 years of suppression for high-risk patients with an excellent or indeterminate response.
✅ Patient Action: Ask your endocrinologist: “What is my current response-to-therapy category, and has my TSH goal been updated to match it?”
Does TSH suppression actually prevent recurrence?
For most survivors, recent evidence shows little recurrence benefit from strong suppression. The clearer benefit appears when cancer has spread beyond the neck.
What recent studies found
In a meta-analysis summarized by the ATA, recurrence risk did not differ significantly at any TSH cutoff. A Memorial Sloan Kettering study followed 771 low- and intermediate-risk patients for a median of six and a half years. Suppression raised osteoporosis risk without changing recurrence.
The exception: cancer that has spread
People with distant spread had significantly more recurrence when TSH stayed at 0.1 mIU/L or higher than when it was kept below 0.1. NCI adds that suppression may improve progression-free survival, but there’s no definitive evidence it extends overall survival.
What your TSH follow-up blood tests will show
Follow-up usually pairs TSH with thyroglobulin, and the ATA advises investigating if either tumor marker rises.
Why the “normal by age” chart isn’t your target
A general chart of TSH levels by age describes people without thyroid cancer. For many survivors, the 2025 goal is your own lab’s assay-specific range, and reference ranges can differ between labs. A “low” flag may match your plan.
TSH, thyroglobulin and antibodies together
Thyroglobulin is made only by well-differentiated thyroid cells. After thyroidectomy, it helps track remaining or returning disease.
📊 Clinical Data Point: Thyroglobulin antibodies occur in 15% to 30% of people with thyroid cancer and can make thyroglobulin results misleading. — Source: Mayo Clinic Laboratories, thyroglobulin tumor marker test catalog
✅ Patient Action: Ask your endocrinologist: “Which reference range does my lab use, and where should my TSH fall within it?”
Side effects of long-term TSH suppression to watch for
Long-term TSH suppression can affect:
- Heart rhythm: including atrial fibrillation
- Bones: bone loss and fractures
- Mood: anxiety and depression
Risk is highest in postmenopausal women, older adults, and people with heart disease or osteoporosis.
Heart rhythm effects
Suppression is linked to atrial fibrillation and reduced cardiac reserve.
⚠️ Clinical Warning: Seek urgent care for chest pain, fainting, sudden breathlessness, or a racing, irregular heartbeat. Never change your levothyroxine dose without your care team.
Bone loss after menopause
In postmenopausal women, suppression is associated with lower bone density and possibly more fractures, although studies disagree. Learn what a T-score of −2.5 means.
Mood and anxiety
Anxiety, depression and reduced quality of life are also reported. See a review of long-term suppression side effects.
TSH suppression and thyroid cancer: common questions
1. Why is TSH suppressed after thyroid cancer?
TSH suppression in thyroid cancer lowers a hormone that can encourage remaining cancer cells to grow. Your endocrinologist decides whether you need it.
2. What should TSH be after thyroidectomy for cancer?
Under 2025 ATA guidelines, TSH should be normal-range for excellent or indeterminate responses and below normal for incomplete responses. Confirm your goal with your endocrinologist.
3. Is TSH suppression still recommended?
Yes, for incomplete responses to treatment. Most other survivors now aim for a normal-range TSH under the 2025 ATA guidelines.
4. How long do you need TSH suppression?
ATA no longer explicitly advises up to 5 years of TSH suppression for high-risk patients with excellent response. Ask your endocrinologist about your timeline.
5. Does TSH suppression prevent recurrence?
A meta-analysis found no recurrence difference at any TSH cutoff overall. Keeping TSH below 0.1 helped only people whose cancer had spread beyond the neck.
6. Can TSH suppression cause heart problems?
Long-term TSH suppression is linked to atrial fibrillation, especially in older adults. Report palpitations to your care team promptly.
7. Does TSH suppression cause bone loss?
Studies link TSH suppression to lower bone density in postmenopausal women. Ask your endocrinologist whether a bone density scan is right for you.
8. What is an excellent response to thyroid cancer treatment?
Broadly, tests show no sign of remaining cancer, so the ATA’s TSH goal becomes the normal range. Your endocrinologist confirms your category.
9. What does thyroglobulin show after thyroid cancer?
Thyroglobulin comes only from thyroid cells, so after thyroidectomy it helps track remaining or returning cancer during follow-up.
10. Do you need TSH suppression after a lobectomy?
After lobectomy, 2025 ATA guidelines use only excellent or structurally incomplete categories. Ask your endocrinologist which TSH goal applies.
11. Is a low TSH dangerous after thyroid cancer?
A low TSH is often intentional after thyroid cancer, but long-term suppression carries heart and bone risks. Review your target with your endocrinologist.
Your next step before your follow-up visit
Your TSH target isn’t fixed for life. Current guidelines reassess it as your response to treatment becomes clear. Bring the two Patient Action questions above to your next endocrinology visit, along with your most recent TSH and thyroglobulin results.
About this content
How this article was put together: researched from recognised health sources, drafted with the help of AI tools, and edited by hand, with sources linked throughout.

Sameer Patel is the founder and editor of My Medicine Advisor. He is not a doctor or medical professional — before starting this site he worked in banking,…
Medical disclaimer
The content on MyMedicineAdvisor is provided for general informational and educational purposes only and is not a substitute for professional medical advice, diagnosis, or treatment. Health information on this website should not be used to diagnose, treat, cure, or prevent any condition without guidance from a qualified healthcare professional. Always seek the advice of your doctor, physician, or another licensed healthcare provider with any questions you may have regarding a medical condition, symptoms, medications, or treatment decisions.